

Professional Introducer Sheath: Key Uses and Selection Tips
2026-09-27
Every successful vascular procedure starts with a reliable introducer sheath—but not all sheaths are created equal. From navigating tortuous anatomy to minimizing insertion trauma, the right professional introducer sheath can make or break your outcomes. Whether you're placing a central line, performing an angiography, or managing complex interventions, understanding key uses and selection criteria is essential. In this post, we'll break down what really matters when choosing a sheath, and why INT has become a trusted name among clinicians who demand precision and durability.
When a Sheath's Design Saves You From a Tough Access
Some vascular targets don't cooperate. The angle is steep, the vessel rolls, or the lumen is barely visible on ultrasound. That's when a sheath's distal taper and stiff inner dilator earn their keep. Instead of pushing the assembly and hoping, you can rely on a gentle transition from wire to sheath that keeps the puncture site stable while you advance.
A well-designed hub also makes a difference. If the sheath body is too flexible, it kinks just past the skin, turning a clean puncture into a frustrating series of readjustments. But with a reinforced strain-relief segment and a low-profile hub that doesn't fight your fingers, you can torque and redirect without losing the wire position. Small details like a side port that clears the drape or a valve that doesn't leak under pressure often decide whether a difficult access becomes a quick save or a prolonged struggle.
In tight, deep, or calcified vessels, these design choices aren't cosmetic. They translate into fewer needle passes, less vessel trauma, and a much better chance of completing the procedure with the patient still calm. That's the moment you appreciate the sheath not as a simple tube, but as the tool that bridges the gap between a tough stick and a secure line.
French Size, Length, and the Anatomy You're Dealing With
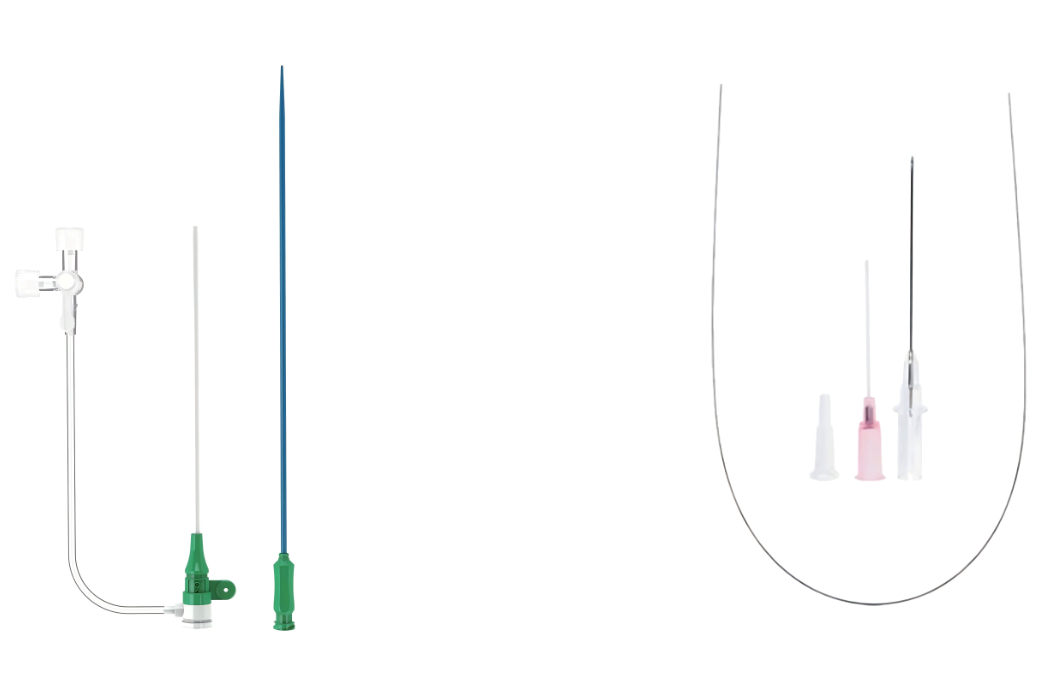
French size refers to the width of a condom laid flat, measured in millimeters—not the length. Most brands list this number on the box, and it usually falls between 49mm and 60mm. Matching it to your girth matters because a condom that’s too tight around the base can feel strangling or break, while one that’s too loose is more likely to slide off. The stretch is forgiving, but only up to a point.
Length gets less attention for good reason: nearly all condoms are longer than an average erection. The extra material either stays rolled at the base or covers a bit more shaft, which is rarely a problem. To find your French size, measure around the thickest part of the erect penis with a soft tape or a strip of paper, then divide that number by two. Pick a condom with a nominal width within a millimeter or two of that figure and adjust from there.
Coatings and Materials: Why Some Sheaths Glide While Others Drag
The difference often comes down to the outermost layer's chemistry and surface texture. A sheath with a low-friction coating, such as a fluoropolymer or a silicone-based additive, reduces the microscopic interlocking between surfaces. That means less resistance when the sheath moves against tissue, another device component, or a guidewire. Drag, on the other hand, typically shows up when the material is tacky, overly soft, or has too high a surface energy, causing it to stick rather than slide.
Material hardness and crosslink density also play a major role. Softer, more elastomeric materials may feel comfortable in the hand but can generate high friction under load. By contrast, a moderately stiffer sheath with a controlled surface roughness can distribute contact pressure more evenly, which prevents the localized stick-slip that creates that dragging sensation. Some manufacturers blend in micronized PTFE or graphite to create a self-lubricating effect without relying on a separate coating that might wear off.
Processing conditions matter just as much as the resin chosen. If the extrusion temperature is too low or the cooling is uneven, the polymer chains can orient in a way that increases surface friction. A well-controlled process yields a smoother, more consistent outer skin, which is why two sheaths made from the same base polymer can feel completely different during insertion. The real engineering art lies in matching the right additive package to the intended clinical use, whether that's a slick introducer sheath or a more tactile access catheter.
Hemostatic Valves Worth Paying Attention To
Most clinicians size up a sheath by its French diameter and coating, but the valve sitting at the hub often decides whether a case flows or fights back. A well-designed hemostatic valve should hold a seal across a 0.014-inch wire, a 6-French guide, and the occasional balloon shaft without weeping around the edges or spiking insertion force. The difference becomes obvious during multiple exchanges: cheaper cross-slit designs start to gape after a single pass of a stent catheter, while reinforced elastomeric seals keep their grip even when you momentarily oversize the device.
Attention also belongs on the side-port geometry and the way the valve handles negative pressure. Valves that sit flush with the sheath hub and offer a low-profile side arm make flushing and contrast injection less turbulent, which matters when you are chasing air bubbles. Some newer designs include a slight pre-slit orientation that allows removal of 0.035-inch wires without tearing, plus a one-handed open position that avoids having to hold the hub with both gloves during device withdrawal. These details rarely make the headline spec sheet, but they are what separate a sheath you forget is there from one you curse on every exchange.
Radiopaque Tips and Tapered Ends: The Practical Payoff
There's a reason experienced clinicians reach for catheters with radiopaque tips when the anatomy gets tricky. The faint glow under fluoroscopy turns guesswork into certainty — you see the tip bend, advance, and settle exactly where it should. No second-guessing, no extra radiation exposure just to confirm placement. It's the kind of quiet reliability that makes a procedure feel less like a gamble and more like a rehearsed routine.
Tapered ends, though, often get less credit than they deserve. A well-designed taper doesn't just ease insertion; it spreads the force over a gentler gradient, reducing the micro-trauma that leads to post-procedure soreness or vessel irritation. Combine that with the radiopaque tip, and you have a catheter that navigates smoothly and tells you precisely where it is at every step. That pairing isn't a luxury — it's a practical payoff for anyone who values efficiency over improvisation.
In practice, the benefit shows up in the smallest moments. A steep bifurcation that would stall a blunt-ended catheter suddenly becomes passable. A difficult angle under live imaging transforms from a source of anxiety into a simple visual task. These design choices don't advertise themselves with flashy features; they simply work, time after time, until you forget what it was like to struggle without them.
Pre-Procedure Compatibility Checks That Prevent Mid-Case Surprises
Compatibility failures rarely announce themselves until the wrong connector meets the wrong port. In many operating rooms, the first sign of trouble is a scope that won't lock into a camera head or a drill bit that doesn't seat properly in a handpiece. These are not exotic problems—they stem from simple oversights in the pre-procedure phase. Checking every physical interface, from fluid warming cassettes to fiber-optic light cables, takes only a few minutes but can save an hour of scrambling once the patient is draped.
A practical approach is to treat the setup area as a test bench, not just a staging zone. Run a quick mock assembly of all powered instruments, tubings, and imaging components before the patient enters the room. Verify that software versions on navigation systems match the implant sets you plan to use, and confirm that backup batteries or power adapters are not just present but actually compatible with the devices they're meant to support. One commonly missed check is the alignment of vendor-specific locking mechanisms—some look identical but will not engage across brands.
Building these checks into a short, visual checklist keeps them from being skipped under time pressure. Photograph the assembled setup and compare it against a reference image from a previous successful case. Assign a circulating nurse or surgical tech to sign off on each connection point, not just the high-risk ones. When incompatibilities are found early, the fix is usually a matter of swapping a cable or an adapter; when found mid-case, that same issue can force a change in surgical plan or an unplanned second setup. Prevention here is not about more paperwork—it's about creating a habit of verifying what you assume will work.
FAQ
Look beyond the outer diameter. A high-quality sheath typically pairs a thin wall with a reinforced coil or braid, letting you gain French size without sacrificing kink resistance. The transition zone at the distal tip matters just as much: a gradual taper and a soft, radiopaque tip help avoid vessel trauma and improve visibility under fluoroscopy. The hemostatic valve should also open and close smoothly without excessive friction on the guidewire or catheter.
Start with the device you plan to pass, not the vessel. Add at least one French size to the largest catheter or balloon you intend to use, so there's still room for contrast injection or pressure monitoring. For working length, map the access point to the target and account for patient body habitus and any tortuosity. In peripheral work, a longer sheath can help you reach the lesion without losing support; in coronary cases, shorter sheaths reduce dead space and improve torque response.
The dilator gradually expands the tissue tract and vessel wall so the sheath tip doesn't catch or buckle. The dilator should protrude just a few millimeters beyond the sheath and fit snugly against the inner lumen—any gap can create a tissue lip that catches on entry. A smooth, low-friction surface on the dilator eases passage, and using a hydrophilic dilator in scarred or calcified access sites can make a noticeable difference.
Peel-away sheaths are worth considering when you need to leave a device in place without removing the sheath over its hub—think pacing leads, tunneled catheters, or implantable ports. The key is to confirm the peel-away split is even and effortless, because a ragged or resistant split can displace the very device you're trying to secure. For routine diagnostic or interventional work where the sheath stays for the case and then is removed, a standard fixed sheath is simpler and costs less.
Kinking at the groin or in a tortuous iliac segment is a frequent problem when a sheath is too soft or too long. It can mimic catheter malfunction and even scrape the vessel wall. Choosing a reinforced sheath with adequate stiffness, or stepping up to a braided design, prevents this. Another issue is bleeding around a poorly designed hemostatic valve—look for valves that hold against backflow even when multiple guidewires are exchanged. Finally, an overly stiff dilator tip can penetrate rather than dilate, so keep the insertion angle shallow and never force the assembly.
Hydrophilic coating reduces friction dramatically when wet, but it can make the sheath slippery at the hub and harder to grip, so some designs coat only the distal segment. Tip geometry matters at two points: the leading edge must be atraumatic, and the transition to the full sheath diameter should be smooth so the sheath doesn't 'snowplow' tissue. In heavily calcified or previously stented vessels, a longer, more flexible tip can help navigate without hanging up on struts.
The valve has to seal around the smallest guidewire and still accommodate the largest device without tearing or leaking. A silicone disc valve is forgiving but may not hold under high venous pressure; a Tuohy-Borst style gives you adjustable compression but adds bulk. If you're using multiple catheters or a side port, check that the side arm doesn't create a low-flow dead zone. For reusables, the valve must be easy to disassemble and clean, or you risk clot formation inside the hub.
The radiopaque marker band location can save time when verifying depth, especially in obese patients. A flexible, kink-resistant strain relief at the hub prevents the sheath from crimping when the patient moves. Surface smoothness on the inner lumen reduces friction during device exchanges, which matters more than most people realize. And if you do interventions, a side port with a stopcock that doesn't snag on drapes or lines can reduce frustration in long cases.
Conclusion
A well-chosen introducer sheath rarely gets the credit it deserves until a difficult access makes you rethink your kit. When the vessel is angled, scarred, or simply unforgiving, a sheath with a tapered end and a tip that shows up clearly under fluoroscopy can mean the difference between a clean pass and repeated attempts. Paying attention to French size against the actual vessel diameter, and matching sheath length to the distance from puncture site to target, prevents unnecessary trauma. Coatings matter too: a hydrophilic coating may glide through tortuous anatomy while an uncoated sheath drags, especially in calcified vessels. Not all coatings behave the same once they dry or meet blood, so testing one before committing to a full tray is worth the time.
Hemostatic valves are another overlooked detail until back-bleeding becomes a nuisance or air embolism becomes a concern. A valve that seals reliably around guidewires, catheters, and even during device exchanges keeps the field cleaner and the procedure calmer. Radiopaque markers on the distal tip offer immediate confirmation of position without extra dye injections. Before starting, run through a short compatibility checklist: Does the sheath accept the intended catheters and devices? Is the sidearm position workable for your setup? Will the dilator and wire pass smoothly? A few minutes spent confirming these details beforehand avoids mid-case surprises that force a sheath exchange or compromise access. The best sheath isn’t the most expensive one, but the one that fits the anatomy, the equipment, and the plan.
Contact Us
Contact Person: Jeffrey
Email: [email protected]
Tel/WhatsApp: 86-0633-2230056
Website: https://www.sd-intmedical.com

